
Conclusion
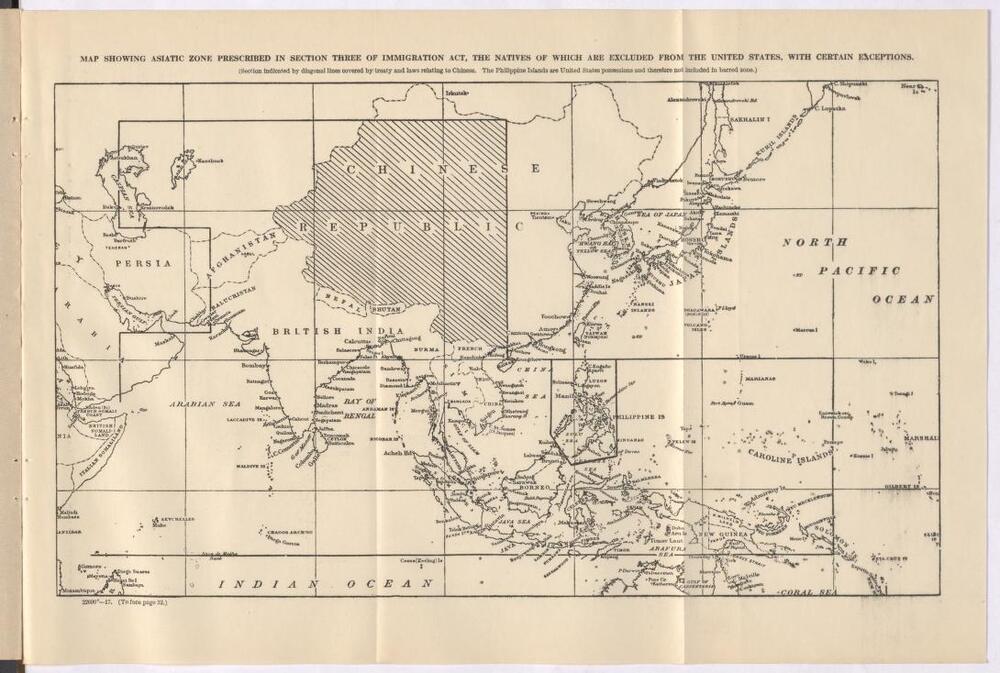
Salmon’s final engagement with immigration came with the 1924 Immigration Act. This Act instituted a system of national quotas which drastically restricted the number of immigrants entering from almost all countries. The quota was deeply racist, with blanket exclusions on people from Asia, Africa, and the Middle East (the so-called “Asiatic Barred Zone”), and it drastically reduced the maximum numbers of immigrants from countries in Southern and Eastern Europe. Immigration from Latin America was not restricted, however, due to the lack of immigration from this region and a desire to preserve “brotherly” ties with Latin American nations (1). The Act also removed the statute of limitations on deportations. Before the Act, the federal government could not deport people if they had been in the country for five years, even if they had come illegally or had chosen not to become citizens. Now, they could be deported even if they had lived in the country for more than five years (2). The Act built upon the 1917 Immigration Act, which had first outlined the geographic extent of the “Asiatic Barred Zone” and instituted a literacy test, requiring immigrants to prove they could read or write in any language (3).
The Act achieved many of the aims of immigration restrictionists and nativists and succeeded in drastically reducing immigration to the United States. Immigration had, after the war, become less important to psychiatrists, who were now tasked with interpreting and describing new war-related psychiatric disorders, such as shellshock. At the same time, public opinion had swung in favor of anti-immigration policy, normalizing many of the measures psychiatrists had advocated for in the early years of the 20th century. This is not to say that psychiatrists completely lost interest in immigration. Indeed, many psychiatrists watched legal developments closely, seeking confirmation of psychiatric expertise in the language of the immigration acts (4). Furthermore, psychiatrists like C. Floyd Haviland were dismayed the Act made no provision for examination and rejection of immigrants at ports of departure, one of the core measures for which Salmon and others had advocated for decades (5). Others, like Spencer L. Dawes, continued to advocate for health-based immigration criteria, including requiring immigrants to submit certificates of health, verified by Public Health Service physicians abroad, before embarkation in Europe (6).
Salmon’s career, to some degree, reflects this progression. After the war, Salmon devoted himself to the institutionalization and formalization of psychiatric education. In this capacity, he tried to attach some of the prestige of specialized medical programs in bacteriology, neurology, and other disciplines to psychiatry. To place psychiatry on this level was the culmination of the hopes of many psychiatrists when Salmon began his career. No longer seeking legitimacy through political issues, psychiatrists could assume a greater role and prominence among medical professionals.
The war played an immense role in this process, as it had in Salmon’s own life. The phenomenon of “war neuroses” or “shellshock” that emerged from the war created a problem only psychiatry could effectively explain and attempt to solve. Psychiatry could, in a very meaningful way, offer hope to veterans traumatized by the violence of conflict and to their families back home, bewildered as to how their sons and loved ones could have changed so dramatically (7).
Salmon no longer wrote extensively on immigration, but his experiences at Ellis Island continued to shape his outlook. The core of his advocacy for veterans relied on the belief that psychiatrists could play a meaningful role in shaping positive social outcomes. Just as in his conviction that psychiatrists should act as the arbiters of admission into this country, expressed all the way back in 1906, Salmon also believed that through the person of the psychiatrist, through one-on-one verbal examination, psychiatrists could bring about improvement in the condition of former soldiers with PTSD. Yet again, this was to be accomplished through the transformation of the environment; more hospitals, more beds, more cleanliness, and more staff. Institutions, when under the direction of experts, could transform patients.
Salmon, for his part, advocated for psychiatric support of the 1924 legislation. In a memorandum to the NCMH drawn up by him, George A. Hastings, and Spencer L. Dawes, he advised the body to "give its full support to... the Johnson Bill and take such steps as it deems proper in securing the enactment into law of the sections described" (8). Salmon encouraged the NCMH to support three features of the Act in particular. These features included the institution of certificates requiring immigrants to verify that they had no family history of mental illness, the provision of ID cards for foreign sailors to prevent desertion in American ports, and the expansion of deportation conditions in order to enshrine mental capacity as a precondition for residence in the US (9). Additionally, he encouraged the NCMH to support New York State in pressuring for reimbursement from the federal government for care of the “alien insane”, to the very exact amount of $17,247,616.71 (10). He also urged the NCMH to seek clarification from legislators as to whether the Act would expand the number of medical personnel tasked with examining immigrants at Ellis Island.
It is interesting to see how Salmon’s support of the 1924 Act, which so profoundly placed political, rather than scientific concerns at the center, remains consistent with his other beliefs. Each of Salmon's recommendations was anticipated in his writings from 1906-1914, and he also had always rationalized the value of quotas. As he had said in 1911, quotas offered “no more profitable field of effort for those who have enlisted in the cause of the prevention of insanity” (11). Salmon only changed his position on immigration certificates. In 1914, Salmon claimed that certificates:
“place a very powerful weapon of oppression in the hands of foreign officials. There is no doubt of the great value to this country of immigrants of the type of Carl Schurz, for instance, but the chances that Carl Schurz would have obtained a favorable certificate of any kind from representatives of the German government when he came to America are very remote” (12).
In supporting the Act, Salmon was aligning himself with eugenicists, nativists, and other xenophobes who, as Adolf Meyer had admitted, were dragging psychiatry into “matters which after all are just a little bit too frankly human and not strict science” (13). In the 1930s, the quotas instituted by the Act contributed to the exclusion of thousands of refugees fleeing a different German regime, that of the Nazis (14). Salmon, with all of his opposition to German imperialism during WWI (15), would no doubt have opposed that regime as well.
A confidence that science could solve social problems, and a supreme confidence in the empirical nature of the expertise of psychiatrists underlies much of the work undertaken by Salmon and his circle. Salmon, his funders, and other medical professionals lacked awareness or interest in interrogating how their cultural beliefs informed their scientific positions. Their positions on immigration exclusion embodied American nativism just as much as it did a form of inductive reasoning. Always starting from the position that a significant portion of immigrants constituted a financial burden on society and a threat to its future prosperity, Salmon and others were always sympathetic to immigrant exclusion. Salmon further saw the value of freeing up government funds through effective exclusion, funds which could be further redirected towards more worthy recipients, like America’s veterans.
Psychiatry treats immigration very differently today. It recognizes the trauma and instability caused by the migration process, its triggers, and the struggles of adjusting to life in a new country. The APA’s Immigration Toolkit, a document outlining basic psychiatric principles around immigration, grounds itself in human rights and legal precedent, introducing The Convention on the Rights of the Child (CRC), unratified by the United States, as the framework in which psychiatrists should operate, and the Flores Settlement (1997) as a benchmark for evaluating US immigration policy in clinical practice. It focuses on how to deal with migrant children and their families, emphasizing the importance of keeping families unified at the border and during the care process. It also stresses the importance of cultural awareness in clinical interactions with immigrant patients:
“Clinical care with migrants must be culturally sensitive, trauma-informed, and intergenerational as they may have experienced discrimination and trauma, have language-barriers and experienced adverse circumstances as a family. Such an approach calls on the family to support one another and heal as a unit” (16).
The Toolkit also emphasizes that “The APA opposes laws, policies, and practices that erode the dignity of and respect for these members of immigrant groups”, centering the needs of immigrants as human beings and as patients (17). In this way, modern psychiatry rejects the oppositional framework employed in Salmon’s time, in which psychiatrists sought to control and regulate immigration to improve America’s own psychiatric developments.
What can Salmon offer us today? During a time when immigration enforcement is increasing, can turning to the infancy of immigration enforcement teach us any lessons? In Salmon’s time, the public’s relationship to medicine was very different than it is today. In his day, the public increasingly embraced the regulative capacity of medicine and its ability to save lives. The government poured money into medical programs, identifying them as ways to accomplish political goals. As funding for medicine today dries up due to social and political change, can psychiatrists rely on the government in the way Salmon ceaselessly did? What alternatives are there?
The COVID-19 pandemic further changed everything. With it came increasing conversations around public health and medicine’s role in society. As medical knowledge is increasingly questioned, and the history of medicine’s role in oppressive systems becomes a greater topic of discussion and reflection, what can the anxieties of Salmon and others about professionalization teach us today? Can they provide a path forward or a way to regain public trust?
Perhaps psychiatrists today can take notes from how Salmon brought psychiatry into the public eye. Salmon showed what can happen if psychiatrists draw immediate, tangible connections between social policy and individual outcomes. He galvanized people, psychiatrists and non-psychiatrists, towards immense interest and concern with psychiatry. In doing so, he dramatically expanded the horizons for psychiatry in America, contributing to the growth of hospitals and education programs even if today, “mental hygiene” is rightfully dismissed as pseudoscientific.
Psychiatrists today are, just as in Salmon’s time, deeply engaged in social questions, including suicide prevention, incarceration, and addiction treatment. Today, the profession champions culturally informed and humble care. Psychiatrists have the unique strength of being close to people’s inner worlds; focusing intensely on the individual, they can move between the clinical and the personal.
What’s different, to some degree, is the platform. Psychiatrists lack access to the halls of power in the same way that Salmon had. Without that access, psychiatrists need to rely on patients, their communities, and the general public to advance programs of care. This is easier said than done, but psychiatrists have the unique strength of being close to people’s inner worlds; focusing intensely on the individual, they can move between the clinical and the personal. By remaining true to this fact, and connecting it with the bigger picture, psychiatrists can, potentially, reclaim some of the role Salmon envisioned for them, embedding psychiatric care in a larger relationship between psychiatry, public health, and civil society.